SKIN CANCERS & CONDITIONS
Dysplastic moles
An unusual-looking mole is assessed by its appearance. A dysplastic naevus is a pathology diagnosis made after tissue is examined under a microscope.
- Common, and most don't develop into melanoma
- Multiple dysplastic moles raise melanoma risk
- May need a biopsy to confirm diagnosis
- Appearance and pathology are different assessments

An unusual-looking mole
An atypical or dysplastic-looking mole may be larger, irregular in shape or colour, or different from your other moles. This is a judgement from appearance, with the naked eye or a dermoscope. Most unusual-looking moles are harmless, but appearance alone cannot confirm what the cells are doing or reliably exclude melanoma.
A pathology diagnosis
If a mole is removed, a pathologist examines the cells under a microscope. The report may describe a dysplastic naevus, graded mild, moderate or severe. This grade describes the cells, rather than how the mole looked.
The distinction matters: a stable unusual-looking mole may be monitored, while a concerning or changing mole may need removal for diagnosis. Your doctor will explain which approach is appropriate.

MBBS, MA (Virtual Comm), Grad Cert Hlth Info, Grad Dip Comp Inf Sci

Dysplastic mole on a man's back
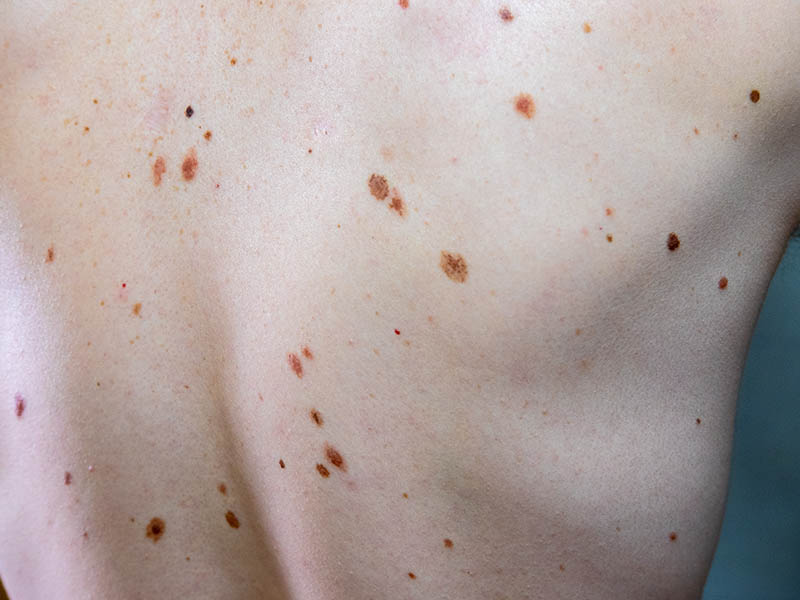
Overview of a man's back with multiple dysplastic moles

Finger pointing at a dysplastic mole
Monitoring and removal
A stable unusual-looking mole may be watched, often with photographs, to detect change. Removal may be recommended if it changes or the doctor is concerned. Removing every unusual-looking mole does not prevent melanoma.
If diagnosis requires tissue, surgical excision allows examination by a pathologist.
What happens after pathology?
The result guides the next step. Many mildly dysplastic moles need no further removal. More severe changes may need wider excision. The decision also depends on the margins, whether any lesion remains and the clinical findings; there is no single re-excision rule for every dysplastic naevus.
Future melanoma risk
People with many atypical or dysplastic moles may have a higher risk of melanoma. Your doctor considers your mole pattern, personal and family history when recommending skin checks and mole mapping.
References
Rosendahl C, Grant-Kels J, Que S, 2015. Dysplastic nevus: Fact and fiction. Journal of the American Academy of Dermatology, volume 73 issue 3, pages 507-512, 1 September 2015. Hocker T, Alikhan A, Comfere N et al, 2013. Favorable long-term outcomes in patients with histologically dysplastic nevi that approach a specimen border Journal of the American Academy of Dermatology volume 68, issue 4, pages 545-551, 1 April 2013. National Cancer Institute, 2022. Common moles, dysplastic nevi, and risk of melanoma.
After a diagnosis of dysplastic mole
Regular skin checks help detect new dysplastic moles or melanomas at an early stage.

Check your skin regularly for new or changing spots. Be alert for “ugly duckling” moles that look different from your other spots.
Your doctor will recommend a skin-check interval according to your mole pattern, personal and family history and other risk factors.
If you have many moles or find it difficult to keep track of them, mole mapping photography can help monitor changes over time.
Concerned about an unusual mole?
Dysplastic moles can resemble melanoma. A skin check with dermoscopy helps determine whether further investigation or monitoring is needed.
Arrange a 1–3 spot assessment